





How do vasectomy reversals work?
Can a vasectomy be reversed?
Often, yes—even many years later. Reversal reconnects the sperm pathway blocked during a vasectomy. The goal is to let sperm enter semen again so you can try for pregnancy through intercourse. Yale Medicine
Two types of microsurgical repair
- Vasovasostomy: reconnects the cut ends of the vas deferens, the tubes that carry sperm.
- Vasoepididymostomy: connects the vas deferens to a tiny tube in the epididymis, where sperm mature, to bypass an additional blockage.
The surgeon examines fluid and sperm findings during surgery to choose the repair. Each side may need a different technique.
Vasectomy reversal success rates
Different definitions of “success”:
- Patency rate: sperm are found in semen after surgery.
- Pregnancy rate: a partner becomes pregnant.
- Live birth rate: a pregnancy results in a baby being born alive.
Ask for results from patients with a similar history, including the repair performed and length of follow-up.
How time since vasectomy affects outcomes
A widely cited study of 1,469 reversals reported the following results. These are historical study findings from 1991, not current Canadian averages or your personal odds.
- Less than 3 years: Sperm returned in 97%; pregnancy reported in 76%.
- 3–8 years: Sperm returned in 88%; pregnancy reported in 53%.
- 9–14 years: Sperm returned in 79%; pregnancy reported in 44%.
- 15 years or more: Sperm returned in 71%; pregnancy reported in 30%.
Years since vasectomy and partner age are material considerations. Longer intervals may mean a more complex repair. They do not automatically rule out reversal. Your partner’s age and fertility also matter, so a percentage based only on years since vasectomy is incomplete.
How much does a vasectomy reversal cost in Canada?
How we estimate surgical costs: Ranges are estimates drawn from our network of 100+ private clinics and surgeons, and they're intentionally broad. Two people seeking the same procedure can receive very different quotes depending on province, surgeon, facility fees, and case complexity. Published prices aren't always comparable either—some are complete bundles, others exclude consultation, imaging, or follow-up. Only the clinic can give you an exact, itemized quote.
Canada private clinics charge $6,000 to $10,000 but the procedure can be as high as $15,000. Costs depend on surgeon, facility, and procedure (vasovasostomy vs vasoepididymostomy).
In the United States, the cost for a vasectomy reversal ranges considerably: CA$7,000–$20,700. The wide range depends on the state of operation, facility, surgeon experience, anesthesia, and reputation premiums (i.e. some high profile fertility clinics charge more).
What’s usually included
- Surgeon fee (vasectomy or microsurgical reversal)
- Facility/clinic fee and nursing
- Local anesthesia (vasectomy) or OR/anesthesia team (reversal)
- Standard disposables/equipment and immediate recovery
- Basic follow-up visit(s) and semen analysis schedule (vasectomy) or initial post-op check (reversal)
What’s sometimes extra (ask in advance)
- Sedation beyond local for vasectomy
- Additional OR time for complex reversal or switching to vasoepididymostomy
- Pathology (if tissue is sent), sperm cryopreservation (if requested), or intraoperative sperm retrieval
- Post-op prescriptions, supplies (support underwear, dressings), and extra semen analyses beyond the standard bundle
- Travel, accommodation, after-hours fees, or extended follow-ups

Vasectomy reversals: what to expect during surgery
Vasectomy reversal (microsurgical)
Surgery takes 2–4 hours (can be longer), done in an operating room with anesthesia.
- Check‑in and plan: Meet anesthesiast and the surgeon; review the plan.
- Anesthesia: You’re asleep or deeply sedated.
- Careful openings: Small incisions are made on the scrotum to reach the vas deferens.
- Test the pathway: The surgeon checks for sperm fluid at the testicular end.
- If sperm are present: Vasovasostomy—the two cut ends of the vas are precisely stitched back together under a microscope.
- If no sperm/there’s a blockage closer to the testicle: Vasoepididymostomy—the vas is connected directly to the epididymis (a finer, more delicate connection).
- Symmetry check: The same is done on the other side, if needed.
- Close up: Layers are closed with fine stitches; a dressing and scrotal support are placed.
- Recovery area: You wake up, review instructions, and go home the same day when stable.
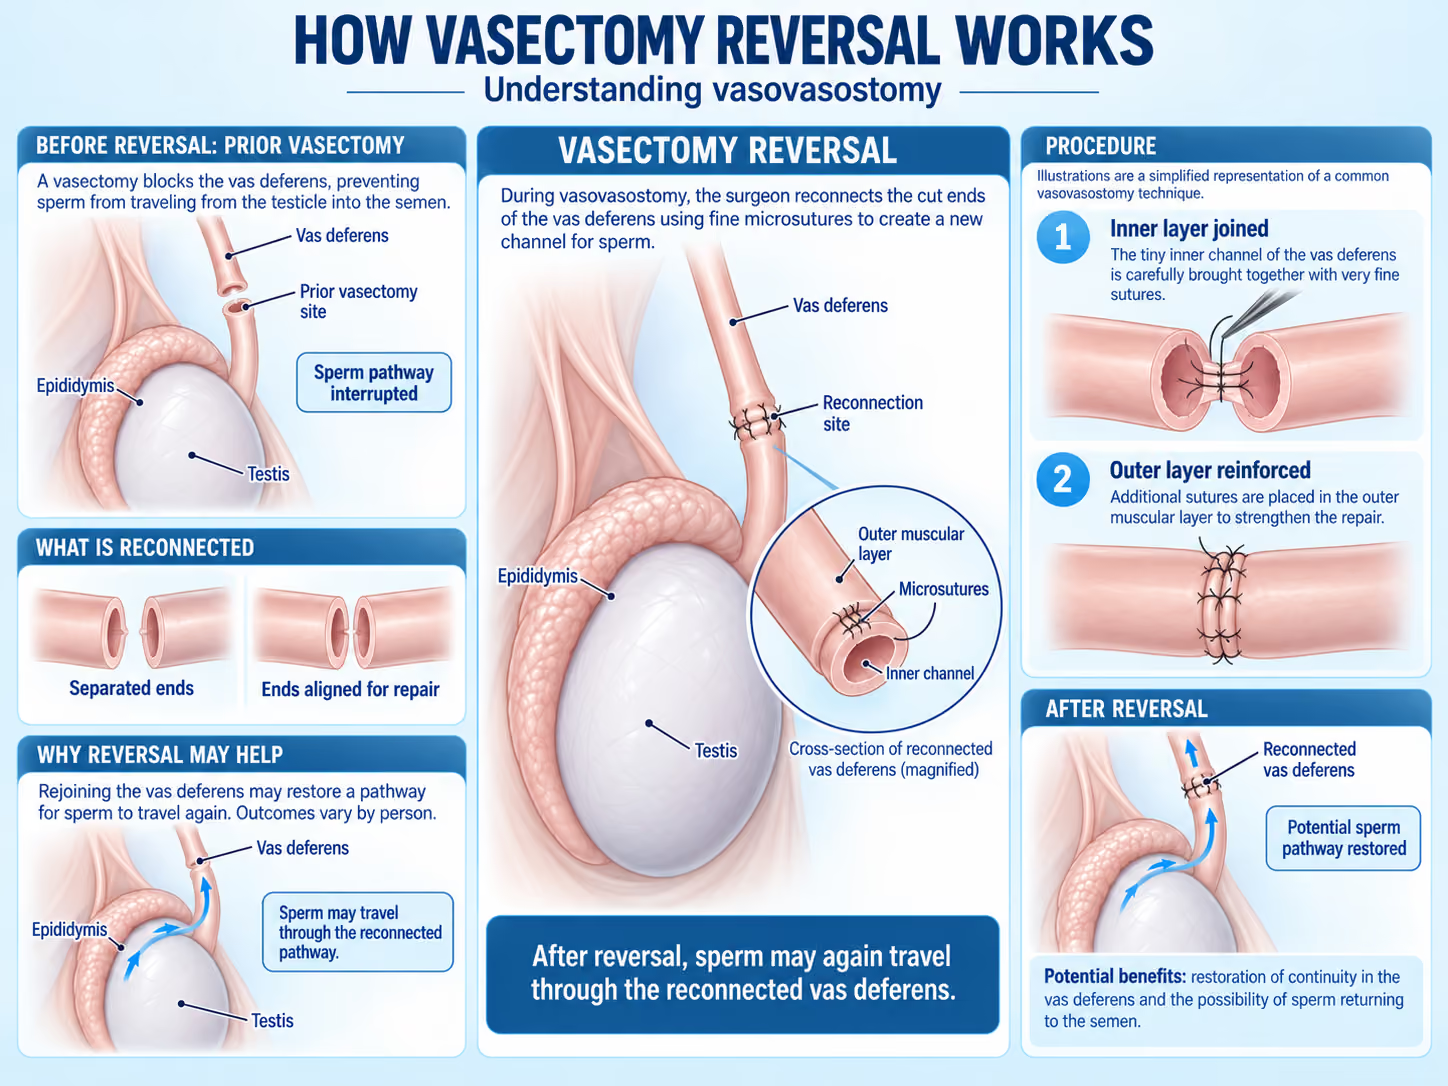
What can I expect from the recovery process?
Everyone heals differently—follow your surgeon’s plan. Taking the instructions seriously usually means a smoother recovery.
Vasectomy reversal (microsurgical)
Week 1
- More swelling and soreness than vasectomy; you’ll move carefully.
- Goals: protect the repair; reduce pain and swelling.
- Activities: scrotal support 24/7, ice as directed, short gentle walks. No lifting >10–15 lb, running, or sex.
Weeks 2–4
- Still cautious but better.
- Activities: increase walking; avoid impact sports, cycling, and heavy lifting. Many return to desk work in 1–2 weeks (earlier for vasectomy).
Weeks 5–8
- Gradual return to full activity when cleared. Sex typically restarted per surgeon guidance; expect a semen analysis schedule to check for sperm.
Red flags—call your care team or seek urgent care
- Fever, spreading redness, pus, or foul odor
- Worsening pain/swelling that doesn’t improve with support/ice
- Large, tense swelling or sudden bruising
- Trouble peeing, dizziness/fainting, or severe nausea/vomiting
Your team will tailor specifics to you—when in doubt, ask before pushing activity.
What is Surgency?
As a family doctor in the public system, I believe transparency is a form of care. I created Surgency to help my patients struggling on long waitlists who wanted to understand all their options for timely medical attention.
Surgency is a free resource designed to empower and educate—helping you understand private pathways and find accredited surgeons within Canada. I hope Surgency brings you clarity.
Dr. Sean Haffey

Is vasectomy reversal covered by provincial insurance (e.g. OHIP, MSP, AHCIP)?
Vasectomy reversal is considered an elective, non-medically-necessary procedure, so it isn't an insured service under OHIP, MSP, AHCIP, RAMQ, or other provincial plans. Because it's uninsured, it can be paid for privately in your own province—you don't need to travel out of province (as is often the case with medically necessary procedures).
How to offset the cost
- Health spending accounts can generally be used to offset the cost of a vasectomy reversal, while private insurance cannot (insurance providers typically exclude this procedure)
- Many Canadians use the Medical Expense Tax Credit (METC) to offset eligible out-of-pocket medical expenses. You can learn more about the METC and how to claim it in our METC Guide.
Coverage rules change and vary by province. Confirm your own situation with your provincial health plan and your surgeon.
Financing and payment plans
Some clinics discuss payment plans or third-party financing. Ask about the interest rate, fees, total repayment and cancellation terms. Availability and approval vary. Read our guide for more info on private surgery financing.
Choosing a surgeon and clinic
Choosing your surgeon is a major benefit of going private—use it to your advantage.
What to look for
Experience and volume
- Ask how many vasectomies and reversals they perform per year.
- For reversals, ask their microsurgical case mix: vasovasostomy vs vasoepididymostomy, one‑sided vs two‑sided, re‑do cases.
- Higher volume and standardized pathways usually correlate with smoother care and fewer complications.
Credentials and training
- Verify licensure with your provincial college (CPSO Ontario, CPSBC BC, CPSA Alberta, CMQ Québec, CPSM Manitoba, etc.).
- Vasectomy: look for FRCSC‑certified urologists or experienced family physicians with focused vasectomy practice and accreditation.
- Reversal: look for FRCSC urologists with fellowship training in microsurgery/andrology.
Outcomes and safety
- Vasectomy: ask about early complication rates (hematoma, infection), need for re‑do, and clearance timeline (semen analysis protocol).
- Reversal: ask patency rate (sperm seen post‑op) and natural pregnancy rates by years since vasectomy; re‑intervention rates.
- Anesthesia safety profile, infection rate, unplanned ER visits/readmissions.
Procedure technique and equipment
- Vasectomy: no‑scalpel access, fascial interposition, intraluminal cautery, open‑ended vs closed‑ended approach—what do they use and why?
- Reversal: microscope (not just loupes), availability to perform vasoepididymostomy if needed, intraoperative sperm assessment, fine sutures, micro‑instruments.
Pre‑op evaluation and planning
- Clear checklist: meds to hold, sedation options, support wear, semen testing schedule (vasectomy) or fertility workup for both partners (reversal).
- For reversal: partner age, prior fertility, hormonal tests if indicated, and realistic timelines.
Facility accreditation
- Confirm clinic/OR accreditation (e.g., CAAASF/Accreditation Canada or provincial non‑hospital surgical facility programs).
- Emergency protocols and hospital transfer agreements.
Care pathway and follow‑up
- Written aftercare, direct contact for urgent questions, and defined follow‑up schedule.
- Semen analysis included? How many tests? Turnaround time? For reversal, planned testing cadence.
Costs and transparency
- Itemized quote: surgeon, facility, anesthesia/sedation, supplies, semen analyses, and any potential add‑ons (e.g., complex reversal time, cryopreservation).
- Cancellation/rescheduling policies and timelines for refunds.
Smart questions to bring to your consult
- How many vasectomies/reversals do you do yearly? What are your recent outcomes (complications, patency/pregnancy rates for reversals)?
- For my situation (years since vasectomy, prior scrotal surgery, partner factors), what technique do you anticipate and why?
- What anesthesia/sedation do you use? How long is the procedure and same‑day discharge plan?
- Exactly what’s included in the price? What could add cost?
- What’s the follow‑up schedule, and who do I contact after hours?
Signals of a high‑quality program
- Publishes or shares outcomes transparently and stratified by case complexity.
- Uses modern, evidence‑based techniques with proper microsurgical equipment for reversals.
- Provides clear, written instructions, direct post‑op contact, and timely lab reporting.
- Offers transparent, itemized pricing and coordinates with your local care team.
If you're currently interested in private surgical pathways within Canada, you can click here for a list of providers.

Frequently asked questions
How do I know if a vasectomy reversal is right for me?
Reversal may suit you if you want pregnancy through intercourse and an assessment supports repairing the sperm pathway. Discuss prior operations, fertility history, years since vasectomy and your family plans. Your partner may also need fertility assessment.
Reversal versus sperm retrieval and IVF
- Vasectomy reversal
- What it involves: Surgery to restore sperm to semen, followed by attempts at pregnancy through intercourse.
- Main consideration: Pregnancy remains dependent on both partners’ fertility.
- Sperm retrieval with IVF and ICSI
- What it involves: Sperm are collected surgically. IVF involves egg collection; ICSI injects a sperm into an egg in the laboratory.
- Main consideration: Treatment involves both partners and may require more than one cycle.
Ask for the full expected cost of each pathway, including medicines, sperm retrieval, egg collection, embryo transfers and storage. IVF may be more suitable when another fertility factor already makes it necessary.
Do I need a referral?
Yes and no—you can reach out to any of the private surgeons listed on Surgency without a referral. Their intake teams are happy to answer questions, explain what they treat, share pricing ranges, and walk you through next steps.
However, to book a formal consultation with the surgeon, you'll typically need a referral from your family doctor or nurse practitioner. Don't have one? Many of the clinics can help coordinate a virtual GP appointment to get the referral paperwork sorted. All surgeons listed on Surgency offer virtual initial consultations, so you don't need to travel until you and the surgeon have agreed on a plan.
Before your consultation, expect the clinic to request relevant medical records and recent diagnostic imaging (X-ray, MRI, CT, ultrasound, lab work, etc.). Having these ready speeds up the process and lets the surgeon give you specific guidance on your very first call.
How do I prepare?
Your urologist’s instructions come first—follow their plan if it differs.
Health prep and optimization
- Medications: Share all prescriptions, OTCs, and supplements. Ask about holding blood thinners (aspirin, warfarin, DOACs), anti-inflammatories, and herbs that increase bleeding. Only stop meds if your doctor says so.
- Stop smoking/vaping: Nicotine impairs healing. Quitting 4+ weeks before helps.
- General fitness: Light cardio, balanced diet, good sleep, and hydration support recovery.
- Medical clearance: Some people need pre-op labs/ECG based on age/health. Bring prior semen analyses or fertility workups (for reversal).
Home prep
- Bathroom/shower: Non-slip mat, easy pump soap, clean towels. Trim (don’t shave) body hair if instructed.
- Comfort kit: Snug supportive underwear or jockstrap, ice packs, small towels, over-the-counter pain meds (if allowed), stool softener.
- Rest zone: Set up a comfy spot with water, snacks, meds, phone/charger, and a small trash bin.
- Clothing: Loose pants/shorts and supportive briefs; avoid tight jeans that rub the incision area.
Support and logistics
- A helper: Arrange a ride home and someone to stay the first 24 hours (both procedures).
- Time off: Vasectomy often needs 1–3 days off desk work; reversal often 1–2 weeks. Plan for lighter duties longer if your job is physical.
- Follow-ups: Book post-op visits and semen testing (vasectomy) or the semen analysis schedule (reversal).
Food, meds, and procedure-day prep
- Fasting: Follow anesthesia instructions. Vasectomy is usually local anesthesia (often no fasting); reversal uses general anesthesia (nothing to eat after midnight; clear liquids per instructions).
- Pain/nausea plan: Pick up approved pain meds and anti-nausea meds if you’ve had issues before.
- Constipation plan: Have a stool softener/fiber on hand, especially after reversal or if taking stronger pain meds.
- Skin prep: Shower the night before and the morning of. No lotions or powders; don’t shave unless told to.
How much does Surgency cost?
Surgency is free for patients, funded for by surgeons.
Surgeons—who meet our listing criteria—pay a flat fee to list on the Surgency platform. To maintain objectivity, there are no commissions, referral fees, nor any ranking or recommending one surgeon over another.
Surgency is patient-first. Our goal is to make the process of finding a private surgeon as simple as possible. You choose who to contact. Learn more in our Advertising Policy.
What are the risks involved?
Your individual risk depends on your health, anatomy, the exact technique (no‑scalpel vasectomy vs microsurgical reversal), anesthesia, and how closely you follow after‑care. Discuss your personal risks with your urologist.
Common and usually temporary (both procedures)
- Pain, swelling, bruising in the scrotum
- Mild bleeding from the small incision(s)
- Skin irritation and tenderness
- Nausea/sleepiness from anesthesia or meds
- Fluid leak from the reconnection that needs attention
- Scar tissue narrowing at the repair site
Less common
- Infection at the incision site
- Hematoma (a firm blood collection causing swelling and pressure)
- Wound healing problems
- Temporary trouble peeing from swelling or pain
- Allergic reaction to meds or local anesthetic
Uncommon but important
- Significant bleeding needing drainage
- Deeper infection requiring antibiotics or a procedure
- Testicular blood‑supply injury leading to atrophy (rare, more relevant in reversals)
- Persistent or worsening pain affecting daily life
How you can lower risk
- Follow pre‑op instructions (medication holds, hygiene)
- Use snug scrotal support, ice, rest, and avoid heavy activity/sex until cleared
- Keep the incision clean and dry; call early for redness, pus, fever, or rapidly increasing swelling
Are vasectomy reversals effective?
60,000 Canadians get vasectomies every year. 2-6% of them will opt for a reversal.
Patency rates (i.e. sperm is present again in ejaculate) are 90-97% for vasovasectomy, and 80-90% for vasoepididymostomy.
But pregnancy ranges between 30-75%—depending heavily on the amount of time since the vasectomy and partner's age.
I still have questions
If you still have questions, then feel free to contact us directly.






